
Health
The Evolution of Growth Factor Therapy: From PRP to PDGF


Quick Answer: Growth factor therapy uses concentrated proteins that signal the body to repair tissue, build collagen, and improve skin and scalp health. The category started with platelet-rich plasma (PRP), advanced with platelet-rich fibrin (PRF), and has now reached a new generation with platelet-derived growth factor (PDGF). Each step forward improved how concentrated, consistent, and patient-friendly the treatment could be. PDGF, particularly in its ReJuveFactor formulation, represents where the field has moved: a standardized growth factor concentrate with significantly higher potency than earlier platelet-based options, no blood draw required, and a hyaluronic acid-enriched formula that supports both rejuvenation and hydration in a single treatment.
Regenerative aesthetics has come a long way in a relatively short period. Twenty years ago, the idea of harvesting growth factors from a patient’s own blood to improve their skin would have sounded niche. Ten years ago, it was becoming mainstream in the form of platelet rich plasma. Five years ago, platelet rich fibrin was emerging as the more refined version. Today, the conversation has expanded again, and platelet-derived growth factor is leading where the next chapter of regenerative skin treatment is heading. Treatments like ReJuveFactor (PDGF) are reshaping what concentrated, standardized growth factor therapy can deliver, and they offer a useful lens for understanding where the category came from and where it is going.
Where the Category Started: Platelet Rich Plasma
Platelet-rich plasma was the first widely adopted form of growth factor therapy in cosmetic medicine. The premise is straightforward. A small sample of blood is drawn from the patient, processed in a centrifuge to separate the platelet-rich layer, and then injected back into the skin or scalp. The platelets carry growth factors that signal the body to build collagen, stimulate hair follicles, and improve overall tissue quality.
PRP earned its place. It has decades of use in sports medicine and orthopedics behind it, and its move into aesthetic dermatology was supported by real clinical results. Patients have seen meaningful improvements in skin texture, mild hair thinning, and post-procedure healing from PRP. The treatment is still offered widely, and for many patients it has been a useful entry point into regenerative care.
What has become clear over time, though, is that PRP has limitations. The growth factor concentration in PRP varies depending on the patient’s biology, the centrifuge protocol, and the processing technique. Two PRP treatments performed at two different clinics can deliver meaningfully different results because the underlying material is not standardized. The growth factors in PRP also release quickly, often within hours, which limits how long the active signal continues to work in the tissue.
The Next Step: Platelet Rich Fibrin
Platelet-rich fibrin emerged as a refinement of the same core idea. The processing is different. Blood is spun at lower speeds without anticoagulants, which preserves more of the natural components and creates a thicker, gel-like concentrate. PRF includes a higher concentration of platelets than PRP, more white blood cells, and a built-in fibrin matrix that the original treatment lacked.
That fibrin matrix is the meaningful upgrade. It acts as a scaffold that traps the growth factors and releases them gradually over a span of days rather than hours. The body has more time to respond to the signal, which translates to more sustained collagen production and longer-lasting visible improvement. PRF has become particularly well-regarded for delicate areas like the under eyes, where its thicker consistency works better than the more fluid PRP, and for hair restoration, where the extended growth factor release supports follicle activity over a longer window.
PRF still requires a blood draw and processing during the appointment, and the final concentrate still depends on what the patient’s blood produces that day. The improvements over PRP are real, but the same underlying constraints around standardization and patient-to-patient variability still apply.
Where the Field Has Moved: Platelet-Derived Growth Factor
Platelet-derived growth factor takes the regenerative concept in a different direction. Instead of harvesting growth factors from the patient’s blood at the time of treatment, PDGF uses a clinically developed, standardized formulation that delivers growth factors at a concentration far beyond what a typical platelet-based treatment can provide. The version used at Skin Rejuvenation Clinic, ReJuveFactor PDGF+, contains growth factor potency reported to be up to three hundred thousand times greater than other platelet-based products.
A few things change as a result of that approach. First, there is no blood draw and no centrifugation step required. The treatment can be delivered directly without the harvesting process that PRP and PRF rely on. Second, the formulation is consistent. Every patient receives the same concentration of active growth factors, which removes the variability that has been a long-standing limitation of platelet-based treatments. Third, the formula is enriched with hyaluronic acid, which adds an immediate hydration and skin barrier benefit on top of the regenerative effect. Few earlier-generation treatments offered both rejuvenation and hydration in a single product.
What This Means for Patient Outcomes
The progression from PRP to PRF to PDGF has tracked closely with what patients have actually been asking for. Earlier treatments delivered real results but required compromises. Patients accepted variability because the alternative was synthetic correction. They tolerated needles and blood draws because the regenerative benefit justified them. They scheduled multiple sessions because the concentration of active material was lower per session.
PDGF reduces several of those compromises at once. The standardized concentration produces more predictable results across patients. The higher growth factor potency means each session delivers more of the active signal that drives skin and follicle response. The hyaluronic acid enrichment delivers visible hydration benefits alongside the regenerative work. Treatment plans are typically two to three sessions spaced eight to twelve weeks apart, with results lasting six to twelve months and maintenance scheduled as needed.
For patients, the practical effect is that a treatment plan built around PDGF tends to deliver more efficient results in fewer sessions, with a more consistent experience between visits.
Where Each Treatment Still Has a Role
The arrival of newer regenerative options does not invalidate what came before. PRP still has clinical evidence behind it and continues to be used effectively in many practices. PRF remains an excellent option, particularly for under-eye work, tear trough volumization with EZ Gel, and patients who specifically prefer treatments derived from their own blood. Both have their place, and both have helped a lot of patients.
What has changed is that PDGF now occupies the position of the most concentrated, most standardized growth factor option available. For patients evaluating regenerative skin care for the first time, or for those who have used earlier platelet-based treatments and are curious about the next generation, PDGF is increasingly the answer.
How to Think About Choosing
A few practical considerations tend to shape the decision. Patients who want the most concentrated growth factor signal possible, who want to avoid a blood draw, or who want the added benefit of hyaluronic acid hydration tend to gravitate toward PDGF. Patients who specifically prefer treatments derived from their own blood, or who need a thicker consistency for areas like the tear trough, are often better suited to PRF. Patients new to regenerative aesthetics are usually best served by a consultation that walks through their specific concerns and matches the treatment to the goal rather than picking a category and working backward.
The category as a whole is in a strong moment. The treatments are biological. The results look like better skin rather than treated skin. And the gap between what patients want and what regenerative aesthetics can deliver continues to close.
The Bigger Picture
The progression from PRP to PRF to PDGF is a useful illustration of how aesthetic medicine evolves. Each generation builds on the last, addresses the limitations the previous version exposed, and creates room for the next refinement. The patients who benefit most are the ones who stay informed about where the field is heading rather than committing permanently to whichever option was leading when they first started treatment.
Growth factor therapy is not a single treatment. It is a category that has been getting better year over year, and the patients who get the most out of it tend to work with experienced providers who can map current options to current goals. PDGF is the most concentrated, most standardized version of that idea available right now. It is unlikely to be the last word, but it is clearly the current one.



The Familiar Tools and the Gaps They Leave
Ask most people to picture a walking aid, and they will describe a wooden cane or a metal walking frame. Both have kept millions of older adults on their feet, yet the range of equipment has grown a great deal, and some of the most useful options look nothing like a traditional mobility aid. A rollator with a built-in seat, a perching stool by the kitchen counter, or a walking chair that lets the user move around the home while seated can each solve problems a cane was never designed to handle.
That matters because mobility after 70 is rarely about one single difficulty. A walking stick works well for someone with mild unsteadiness or a sore knee on one side. It takes some weight off the weaker leg and gives the brain an extra point of contact with the floor, which improves balance. What it cannot do is offer much support when legs are tired, and it keeps one hand permanently occupied.
A walking frame, often called a Zimmer frame in the UK, provides far more stability. The trade-off is that it needs both hands, has to be lifted with every step and can be awkward in narrow hallways or small bathrooms. Many people quietly develop a risky habit of leaving the frame behind so they can carry a cup of tea or a plate, which is exactly the moment a fall is most likely.
Rollators sit somewhere in between. With three or four wheels, hand brakes and usually a seat and basket, they are excellent for the high street, the park or a trip to the shops. Indoors they can feel bulky, and they demand enough grip strength to operate the brakes reliably.
The real gap appears in everyday household tasks. Cooking, washing up, unpacking shopping and reaching into low cupboards all require free hands and the ability to stay upright for several minutes. For many people over 70, fatigue rather than balance is what limits these jobs, and that is where newer types of equipment have started to fill in.
Matching the Aid to the Task, Not Just the Person
A helpful way to think about mobility equipment is to start with the activity rather than the diagnosis. Instead of asking “what walking aid do I need?”, it is often more productive to ask what happens in each room of the house and where things become difficult. The answers tend to point towards a small collection of aids, each suited to a particular setting.
In the kitchen, the challenge is usually standing still for long periods while using both hands. A perching stool lets someone lean rather than stand, and seated mobility solutions allow a person to move between the hob, the sink and the fridge without getting up each time. In the bathroom, grab rails, a shower stool and a raised toilet seat do more for safety than any walking aid could. On the stairs, a second banister or a stairlift removes the need to carry anything at all. Outside the home, a lightweight folding rollator or, for longer distances, a mobility scooter may be the better choice.
Ending up with two or three different aids is normal and sensible. The most capable manufacturers acknowledge this openly. The walking aids guide from VELA, written by one of the company’s occupational therapists, states plainly that its chair may not fully replace a rollator for trips outside the home. Instead, it presents the chair as an indoor aid that lets users move around with their feet while seated, lock the wheels with a handbrake and use an electric seat lift to reach both high shelves and low drawers. That kind of candour is useful for buyers, because it shows where a product genuinely fits instead of promising that one device will do everything.
Before buying anything, a few practical questions are worth asking. Will it fit through every doorway in the house, including the bathroom? How does it cope with rugs, thresholds and different floor surfaces? Are the brakes easy to use with stiff or arthritic hands? How much does it weigh if it ever needs to be lifted into a car? Is there a trial period or a returns policy? Testing equipment in the actual home, rather than in a showroom with smooth floors and wide aisles, often reveals problems that a product description never mentions.
Keeping Strength and Confidence While the Aids Do Their Part
A walking aid should support activity, not replace it. One of the quiet risks in later life is that equipment makes things so easy that muscles gradually weaken from lack of use. The aim is to use aids for the moments when they genuinely reduce risk or save energy, while still giving the legs regular work to do.
UK physical activity guidelines advise older adults to include activities that improve strength, balance and flexibility on at least two days a week. This does not need to mean a gym membership. Standing up from a chair several times in a row, heel raises while holding the kitchen worktop and slow side steps along a hallway all build the strength that keeps walking safe. Local councils, community centres and charities often run gentle exercise classes designed specifically for older people, and these have the added benefit of getting people out of the house and talking to others.
Professional advice makes a real difference here. A GP can refer someone to a physiotherapist for a walking and balance assessment, and the local council’s adult social care team can usually arrange a visit from an occupational therapist who looks at the home itself. These assessments often lead to simple equipment being loaned or fitted, and they help avoid buying the wrong product. A physiotherapist will also check that a walking stick is set to the right height, which is typically level with the crease of the wrist when the arm hangs loosely.
Equipment needs looking after too. Rubber ferrules on sticks and frames wear down and lose grip, brake cables on rollators can loosen, and wheels collect hair and dust that make them stiff. A quick check every few months keeps everything working as intended.
Finally, it pays to review the whole setup regularly, and always after a fall, an illness or a hospital stay. Needs change, sometimes for the better as strength returns and sometimes as energy dips. Fear of falling can lead people to move less, which in turn makes falls more likely. The right combination of aids, combined with regular movement, breaks that cycle and allows people to stay active, independent and confident in their own homes for longer.


International patients considering cosmetic surgery often compare different destinations before deciding where to have treatment. Poland and Turkey are two countries that may appear during this research, with clinics offering a variety of cosmetic procedures to international patients.
However, comparing destinations involves more than looking at advertised prices. Patients should consider surgeon qualifications, clinic facilities, consultation processes, travel arrangements, recovery, and aftercare.
Comparing the Medical Environment
The first step is to research individual clinics and surgeons in both countries. Healthcare standards and services can differ between providers, so patients should avoid making assumptions based solely on the destination.
When comparing clinics, consider:
- Surgeon qualifications
- Professional registration
- Experience with the selected procedure
- Surgical facilities
- Anesthesia arrangements
- Postoperative monitoring
- Follow-up care
Plastic Surgery Turkey: What Patients Should Research
Plastic surgery turkey is frequently considered by international patients looking for cosmetic procedures abroad. Turkey has clinics that specifically work with international patients, but individual providers should still be researched carefully.
Before booking, patients can ask about the surgeon’s experience, the location of the surgery, available aftercare, and the length of stay recommended after the procedure.
Cosmetic Surgery Turkey Packages
People searching for cosmetic surgery trukey may find treatment packages that combine surgery with services such as accommodation and transportation.
Patients should check exactly what is included in these packages. A package may cover some travel-related services while other expenses remain separate.
Useful questions include:
- Is the consultation included?
- Are medical tests included?
- Is anesthesia included?
- Are medications included?
- How many accommodation nights are provided?
- Are postoperative appointments included?
- What happens if an additional stay is needed?
Understanding Plastic Surgery in Poland
Poland is another destination that international patients may consider for cosmetic procedures. Patients researching Polish clinics should apply the same level of scrutiny when checking surgeons and facilities.
The consultation should provide information about the proposed procedure, expected recovery, potential risks, and aftercare.
Patients should also confirm where the surgery will take place and who will be responsible for postoperative monitoring.
Comparing the Plastic Surgery Price
The plastic surgery price can vary considerably in both Poland and Turkey. The final amount may depend on the procedure, surgeon, clinic, anesthesia, medical tests, and aftercare.
Instead of comparing only the advertised surgery fee, patients should request a complete quotation.
Possible expenses include:
| Cost | What to Check |
| Surgery | What procedure is included |
| Consultation | Whether consultation fees apply |
| Anesthesia | Whether it is part of the quotation |
| Tests | Required preoperative examinations |
| Medication | Included or charged separately |
| Aftercare | Number of follow-up appointments |
| Accommodation | Number of included nights |
| Transportation | Airport and local transfers |
| Flights | Usually a separate travel expense |
Travel Considerations
The distance between the patient’s home and the destination can affect the overall planning process. Patients should consider flight duration, transportation, accommodation, and the time required to recover before traveling home.
A shorter journey may be more convenient for some patients, while others may prioritize different factors.
The surgeon should provide specific guidance about when travel is appropriate after surgery.
Recovery and Aftercare
Recovery is an important part of any cosmetic surgery trukey journey. Patients should understand how long they may need to remain in Poland or Turkey before returning home.
Ask the clinic about:
- Expected recovery time
- Follow-up appointments
- Medication
- Activity restrictions
- Postoperative monitoring
- Emergency contact arrangements
Patients should also understand what support is available once they return home.
Communication With the Clinic
International patients should be able to communicate clearly with their medical team. Before booking, it can be useful to establish who will handle questions before surgery and who will provide postoperative support.
Patients should receive clear written information about the treatment plan, costs, preparation, and recovery instructions.
Accommodation During Recovery
Accommodation should be selected with recovery in mind. Staying close to the clinic may make follow-up appointments easier and reduce unnecessary transportation.
Patients may want to consider:
- Distance from the clinic
- Accessibility
- Comfortable sleeping arrangements
- Transportation options
- Nearby pharmacies and shops
- Flexible booking policies
What International Patients Should Compare
Rather than asking which destination is universally suitable, patients can create a personal comparison based on the information available from individual clinics.
Consider these categories:
Medical: Qualifications, experience, facility, procedure, and aftercare.
Financial: Complete treatment cost, accommodation, travel, medication, and potential additional expenses.
Practical: Travel time, communication, recovery period, and follow-up arrangements.
Questions to Ask Before Choosing
Before making a booking in either Poland or Turkey, patients can ask:
- Who will perform my surgery?
- What qualifications and experience do they have?
- Where will the procedure take place?
- What is included in the quoted price?
- How long should I stay after surgery?
- What aftercare is provided?
- What happens if I need additional medical attention?
- What costs are not included?
Getting clear answers can make it easier to understand the differences between individual providers.
Conclusion
Poland and Turkey are both destinations that international patients may consider when researching cosmetic surgery abroad. The most useful comparison should focus on individual surgeons and clinics, rather than relying only on the country or advertised package.
Patients researching Plastic surgery turkey or cosmetic surgery trukey should examine qualifications, facilities, recovery arrangements, and aftercare. They should also look beyond the advertised plastic surgery price and calculate the complete cost of treatment, travel, accommodation, and postoperative care.

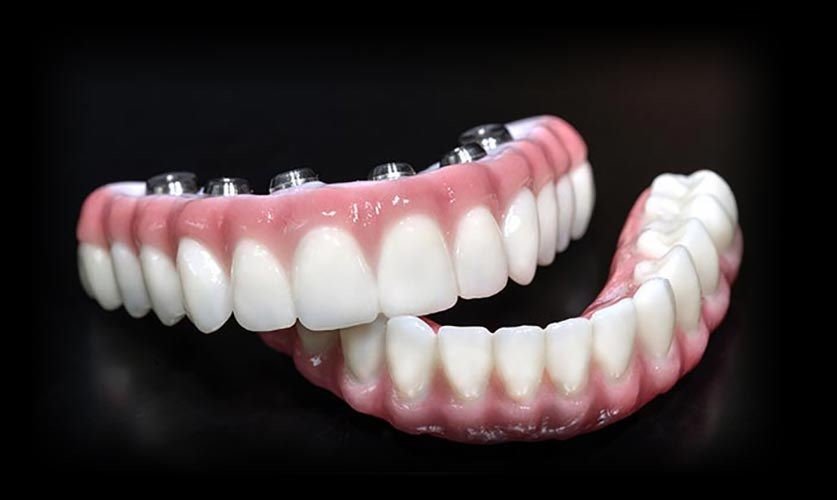
When most or all teeth in one jaw are missing, the choice is not simply between “removable” and “permanent” teeth. Conventional dentures and implant-supported fixed bridges differ in how they stay in place, what treatment involves and how they must be cleaned. Both can restore a usable smile, but neither suits everyone. Understanding the practical trade-offs can help you have a more useful conversation with a dentist about your health, priorities and budget.
What each option involves
A conventional full denture is a removable set of replacement teeth resting on the gums. Its fit depends on the shape of the jaw and surrounding tissues; some people also use denture adhesive. A denture can usually be made without implant surgery, although any teeth requiring removal must be addressed first. It may need adjustments as the gums and jaw change shape over time.
A fixed full-arch bridge attaches to dental implants placed in the jawbone. It stays in place for daily activities and is removed by a dental professional when necessary, rather than by the wearer each night. The number and position of implants depend on an individual assessment. An implant-retained overdenture is another possibility: implants help secure it, but the wearer still takes it out for cleaning.
How they feel and function day to day
Stability and eating
A well-fitting denture can work well, particularly after someone has had time to adapt. Even so, it may shift during chewing or speaking, especially as its fit changes. A fixed bridge generally feels more stable because the implants support it. That does not mean every food is immediately comfortable or that implant restorations are indestructible. Materials, bite forces and any advice given during healing still matter.
Coverage and appearance
An upper conventional denture commonly covers part or all of the palate. Some wearers find this affects their sense of taste, speech or comfort. A fixed bridge usually leaves the palate uncovered, although its shape must still allow effective cleaning. Either option can be designed with attention to tooth position and facial support. The most natural-looking result depends on careful planning, not the label attached to the treatment.
Getting used to a new restoration
Speech can take practice with either approach. Denture wearers also learn how to insert, remove and store their appliance. A fixed bridge avoids those daily steps, but it brings different responsibilities around cleaning beneath the teeth. If hand dexterity or access to support is a concern, ask to see exactly what the proposed routine would involve before deciding.
Treatment demands and suitability
Dentures can often be provided without the surgical stages involved in implants. If teeth have recently been extracted, however, the gums and jaw may continue changing during healing. An immediate denture can therefore need relining or replacement. The timeline for a fixed bridge varies too: assessment, scans, possible extractions, implant placement and a provisional restoration may all be part of the plan.
Implants require enough suitable bone and healthy surrounding tissues, or a plan that accounts for limitations. Medical conditions, smoking, medicines and a history of gum disease may affect risks or healing. A dentist can explain whether a fixed approach, including all on 4 treatment, is appropriate after examining your mouth and reviewing your health history. No particular technique guarantees immediate fixed teeth or eliminates complications.
Maintenance is different, not optional
Removable dentures should be cleaned as directed, taken out when recommended and checked for wear or poor fit. Continuing to use a loose denture can cause discomfort, so new sore spots deserve attention. The mouth also needs routine examination, even when no natural teeth remain. If a denture breaks, avoid attempting a home repair that could change its fit.
Fixed bridges cannot be removed for ordinary cleaning. Food and plaque can collect around implants and beneath the bridge, making suitable brushes, flossing aids or other recommended tools important. Regular professional reviews help monitor the bridge, implants and surrounding tissues. Components may need maintenance or replacement over time; implants themselves can also develop problems. “Fixed” describes how the teeth attach, not freedom from ongoing care.
Understanding the full cost
Conventional dentures generally have a lower upfront price than implant surgery and a fixed bridge. Their longer-term costs may include adjustments, relines and eventual replacement. Implant treatment usually involves a larger initial commitment and may also require scans, provisional teeth, maintenance or repairs. Request a written estimate that separates each stage and explains what happens if the proposed plan changes.
In Australia, private health insurance benefits vary by fund, policy and treatment category, and waiting periods or annual limits may apply. Ask your fund about specific item numbers rather than assuming a quoted procedure is covered. Medicare generally does not cover routine dental care for adults, though eligibility for particular public or other schemes depends on individual circumstances. Cost matters, but it should be weighed alongside suitability and the care required afterward.
Questions worth taking to a consultation
Ask what findings support the recommended option, what alternatives remain reasonable and which parts of treatment are uncertain. Find out how long you might be without your final teeth, what you could eat during recovery and how complications would be managed. For a fixed bridge, request a demonstration of cleaning beneath it; for a denture, ask how fit will be reviewed as your mouth changes.
The better choice is the one that fits your clinical situation and everyday life, not simply the option that sounds more advanced. A clear comparison should leave you understanding the treatment steps, likely maintenance and total financial commitment, with room to seek a second opinion if you need one.

Account Safety 101: How to Vet Any Instagram Growth Service

What Makes Underground Streetwear Hit? Breaking Down the MF DOOM Shirt and Parke Hoodie Hype

Unlocking Peak Performance with AMD Ryzen X3D: A Gamer’s Ultimate Guide

5 questions every Sydney homeowner should ask before hiring a plumber

Transforming Business Efficiency with Modern Workplace Solutions

Empowering Success: Comprehensive NDIS Student Support Services

The 15 Highest-Paid Rugby Players in the World

Christopher Dare: The Untold Story of Engineer and Former Husband of Angela Rippon

How to Ensure Your Home is Valued Correctly for a Quick Sale

What Is Fanquer? The Digital Creator Platform Transforming Direct-to-Fan Engagement

Dr Jared Ross: Missouri Appeals Court Upholds Protection Order Over Graphic Torture and Murder Threats

Nancy Hallam: The Inspiring Life, Career, and Success Story Behind Ian Wright’s Wife
The 15 Highest-Paid Rugby Players in the World
Christopher Dare: The Untold Story of Engineer and Former Husband of Angela Rippon
How to Ensure Your Home is Valued Correctly for a Quick Sale
What Is Fanquer? The Digital Creator Platform Transforming Direct-to-Fan Engagement
Dr Jared Ross: Missouri Appeals Court Upholds Protection Order Over Graphic Torture and Murder Threats
Nancy Hallam: The Inspiring Life, Career, and Success Story Behind Ian Wright’s Wife
-
 Sports5 months ago
The 15 Highest-Paid Rugby Players in the World
-
Celebrity10 months ago
Christopher Dare: The Untold Story of Engineer and Former Husband of Angela Rippon
-
 Real Estate8 months ago
How to Ensure Your Home is Valued Correctly for a Quick Sale
-
 Technology4 months ago
What Is Fanquer? The Digital Creator Platform Transforming Direct-to-Fan Engagement
-
 Celebrity4 months ago
Dr Jared Ross: Missouri Appeals Court Upholds Protection Order Over Graphic Torture and Murder Threats
-
Celebrity11 months ago
Nancy Hallam: The Inspiring Life, Career, and Success Story Behind Ian Wright’s Wife
-

 Health9 months ago
Enclomimed 25 (Enclomiphene) – Effective PCT Protocol
-
 Celebrity11 months ago
Who Is Maisie Mae Roffey? The Private Life, Family Story, and Quiet Success of Julie Walters’ Daughter